"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="WxV_IOPE7-2309410982-linear-gradient" x1="1" x2="0" y1="0.5951279047551217" y2="0.4048720952448783"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="WwbAIQIz8-2309410982-linear-gradient" x1="0.43478742751482424" x2="0.6358595260107829" y1="0.26" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="ZWsVQcPfn-2309410982-linear-gradient" x1="0.9508213454678907" x2="0.04917865453210929" y1="0" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="lTyCGrzzP-2309410982-linear-gradient" x1="0.374937164194436" x2="0.625062835805564" y1="0" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient></defs><g d="M 658.002 1357.705 C 1020.321 1357.705 1314.04 1063.989 1314.04 701.667 C 1314.04 339.347 1020.321 45.626 658.002 45.626 C 295.681 45.626 1.96 339.347 1.96 701.667 L 0 701.667 C 0 338.263 294.598 43.665 658.002 43.665 C 1021.404 43.665 1316 338.263 1316 701.667 C 1316 1065.072 1021.404 1359.672 658.002 1359.672 C 294.598 1359.672 0 1065.072 0 701.667 L 1.96 701.667 C 1.96 1063.989 295.681 1357.705 658.002 1357.705 Z M 658.005 1265.053 C 969.154 1265.053 1221.392 1012.819 1221.392 701.667 C 1221.392 390.517 969.154 138.281 658.005 138.281 C 346.856 138.281 94.619 390.517 94.619 701.667 L 92.659 701.667 C 92.659 389.433 345.77 136.321 658.005 136.321 C 970.241 136.321 1223.352 389.433 1223.352 701.667 C 1223.352 1013.902 970.241 1267.017 658.005 1267.017 C 345.77 1267.017 92.659 1013.902 92.659 701.667 L 94.619 701.667 C 94.619 1012.819 346.856 1265.053 658.005 1265.053 Z M 658.002 1166.116 C 914.513 1166.116 1122.452 958.178 1122.452 701.667 C 1122.452 445.16 914.513 237.22 658.002 237.22 C 401.494 237.22 193.551 445.16 193.551 701.667 L 191.59 701.667 C 191.59 444.077 400.411 235.255 658.002 235.255 C 915.596 235.255 1124.412 444.077 1124.412 701.667 C 1124.412 959.261 915.596 1168.084 658.002 1168.084 C 400.411 1168.084 191.59 959.261 191.59 701.667 L 193.551 701.667 C 193.551 958.178 401.494 1166.116 658.002 1166.116 Z M 281.657 818.28 C 298.572 818.28 314.804 825.001 326.765 836.965 L 458.99 969.182 C 470.582 980.781 486.308 987.298 502.706 987.298 L 612.137 987.298 C 646.284 987.298 673.972 959.61 673.972 925.463 L 673.972 891.504 L 675.939 891.504 L 675.939 925.463 C 675.939 960.7 647.374 989.258 612.137 989.258 L 502.706 989.258 C 485.788 989.258 469.562 982.537 457.599 970.573 L 325.378 838.356 C 313.785 826.757 298.056 820.242 281.657 820.244 L 1.173 820.244 L 1.173 818.28 Z M 746.64 888.714 L 1053.046 888.714 C 1069.967 888.714 1086.194 895.435 1098.16 907.398 L 1259.381 1068.619 L 1257.99 1070.007 L 1096.772 908.79 C 1085.175 897.193 1069.446 890.679 1053.046 890.681 L 746.64 890.681 C 729.724 890.681 713.493 883.957 701.533 871.993 L 685.377 855.845 L 686.769 854.453 L 702.917 870.605 C 714.513 882.201 730.241 888.715 746.64 888.714 Z M 667.685 552 L 512.316 396.894 C 494.66 379.264 484.741 355.356 484.739 330.426 L 484.739 0 L 487.632 0 L 487.632 330.426 C 487.632 354.592 497.248 377.763 514.369 394.851 L 669.739 549.957 Z M 782.851 700.491 C 816.998 700.491 844.686 672.804 844.686 638.655 L 844.686 516.468 C 844.687 499.547 851.409 483.32 863.374 471.355 L 1177.508 157.22 L 1178.896 158.607 L 864.762 472.742 C 853.162 484.337 846.646 500.067 846.646 516.468 L 846.646 638.655 C 846.646 673.89 818.088 702.455 782.851 702.455 L 700.405 702.455 L 700.405 700.491 Z M 130.338 534.223 L 213.07 534.223 C 256.112 534.223 291.003 569.114 291.003 612.156 L 291.003 694.888 C 291.003 711.29 297.514 727.017 309.113 738.611 L 472.887 902.378 L 471.496 903.769 L 307.726 739.995 C 295.761 728.033 289.038 711.807 289.038 694.888 L 289.038 612.156 C 289.038 570.198 255.028 536.188 213.07 536.188 L 130.338 536.188 C 113.419 536.187 97.193 529.465 85.23 517.5 L 77.071 509.345 C 65.107 497.381 58.386 481.153 58.388 464.233 L 58.388 199.526 L 60.348 199.526 L 60.348 464.233 C 60.349 480.631 66.863 496.358 78.458 507.954 L 86.617 516.113 C 98.213 527.709 113.94 534.223 130.338 534.223 Z" fill="transparent" height="1359.6717183844698px" id="DcyumyANr" transform="translate(0 -43.665)" width="1316px"><g opacity="0.5"><path d="M 658.002 1314.039 C 1020.321 1314.039 1314.04 1020.324 1314.04 658.001 C 1314.04 295.681 1020.321 1.961 658.002 1.961 C 295.681 1.961 1.96 295.682 1.96 658.001 L 0 658.001 C 0 294.598 294.598 0 658.002 0 C 1021.404 0 1316 294.598 1316 658.001 C 1316 1021.407 1021.404 1316.007 658.002 1316.007 C 294.598 1316.007 0 1021.407 0 658.001 L 1.96 658.001 C 1.96 1020.324 295.681 1314.039 658.002 1314.039 Z" fill="rgb(255, 255, 255)" height="1316.0065114752902px" id="dxf13D52Y" transform="translate(0 43.665)" width="1316px"/></g><g opacity="0.3"><path d="M 565.347 1128.732 C 876.496 1128.732 1128.733 876.498 1128.733 565.346 C 1128.733 254.196 876.496 1.961 565.347 1.961 C 254.197 1.961 1.961 254.196 1.961 565.346 L 0 565.346 C 0 253.112 253.111 0 565.347 0 C 877.582 0 1130.693 253.112 1130.693 565.346 C 1130.693 877.581 877.582 1130.696 565.347 1130.696 C 253.111 1130.696 0 877.581 0 565.346 L 1.961 565.346 C 1.961 876.498 254.197 1128.732 565.347 1128.732 Z" fill="rgb(255, 255, 255)" height="1130.6960934794101px" id="if1BmYw1S" transform="translate(92.659 136.321)" width="1130.693351805604px"/></g><g opacity="0.15"><path d="M 466.412 930.861 C 722.923 930.861 930.862 722.922 930.862 466.411 C 930.862 209.905 722.923 1.965 466.412 1.965 C 209.904 1.965 1.961 209.905 1.961 466.411 L 0 466.411 C 0 208.822 208.821 0 466.412 0 C 724.006 0 932.822 208.822 932.822 466.411 C 932.822 724.005 724.006 932.828 466.412 932.828 C 208.821 932.828 0 724.005 0 466.411 L 1.961 466.411 C 1.961 722.922 209.904 930.861 466.412 930.861 Z" fill="rgb(255, 255, 255)" height="932.8284667407987px" id="ef75NsYf6" transform="translate(191.59 235.255)" width="932.8219552655086px"/></g><g opacity="0.5"><path d="M 280.484 0 C 297.399 0 313.63 6.721 325.592 18.685 L 457.817 150.902 C 469.408 162.501 485.135 169.018 501.533 169.017 L 610.964 169.017 C 645.111 169.017 672.799 141.33 672.799 107.182 L 672.799 73.223 L 674.766 73.223 L 674.766 107.182 C 674.766 142.42 646.201 170.978 610.964 170.978 L 501.533 170.978 C 484.614 170.978 468.389 164.257 456.426 152.293 L 324.205 20.076 C 312.611 8.477 296.883 1.961 280.484 1.964 L 0 1.964 L 0 0 Z" fill="url(%23cQ4xRdUtr-2309410982-linear-gradient)" height="170.97763275969464px" id="cQ4xRdUtr" transform="translate(1.173 818.28)" width="674.7656780356198px"/></g><g opacity="0.5"><path d="M 61.263 34.261 L 367.669 34.261 C 384.589 34.261 400.817 40.982 412.783 52.945 L 574.004 214.166 L 572.612 215.554 L 411.395 54.337 C 399.798 42.74 384.069 36.226 367.669 36.228 L 61.263 36.228 C 44.347 36.228 28.116 29.504 16.155 17.54 L 0 1.391 L 1.391 0 L 17.54 16.152 C 29.136 27.747 44.864 34.261 61.263 34.261 Z" fill="url(%23WxV_IOPE7-2309410982-linear-gradient)" height="215.55382175474415px" id="WxV_IOPE7" transform="translate(685.377 854.453)" width="574.0036823012563px"/></g><g opacity="0.5"><path d="M 182.946 552 L 27.577 396.894 C 9.921 379.264 0.002 355.356 0 330.426 L 0 0 L 2.893 0 L 2.893 330.426 C 2.893 354.592 12.509 377.763 29.63 394.851 L 185 549.957 Z" fill="url(%23WwbAIQIz8-2309410982-linear-gradient)" height="552px" id="WwbAIQIz8" transform="translate(484.739 0)" width="185px"/></g><g opacity="0.5"><path d="M 82.446 543.271 C 116.593 543.271 144.281 515.583 144.281 481.435 L 144.281 359.248 C 144.282 342.327 151.004 326.1 162.969 314.135 L 477.103 0 L 478.491 1.387 L 164.356 315.522 C 152.757 327.117 146.241 342.846 146.241 359.248 L 146.241 481.435 C 146.241 516.67 117.683 545.235 82.446 545.235 L 0 545.235 L 0 543.271 Z" fill="url(%23ZWsVQcPfn-2309410982-linear-gradient)" height="545.2346136318063px" id="ZWsVQcPfn" transform="translate(700.405 157.22)" width="478.4906210693257px"/></g><g opacity="0.5"><path d="M 71.95 334.696 L 154.682 334.696 C 197.724 334.696 232.616 369.588 232.616 412.63 L 232.616 495.362 C 232.616 511.764 239.126 527.491 250.725 539.084 L 414.5 702.851 L 413.108 704.243 L 249.338 540.469 C 237.373 528.507 230.651 512.281 230.651 495.362 L 230.651 412.63 C 230.651 370.672 196.64 336.661 154.682 336.661 L 71.95 336.661 C 55.031 336.661 38.805 329.939 26.843 317.974 L 18.683 309.819 C 6.719 297.854 -0.001 281.627 0 264.707 L 0 0 L 1.961 0 L 1.961 264.707 C 1.961 281.105 8.475 296.832 20.07 308.428 L 28.229 316.587 C 39.825 328.182 55.552 334.697 71.95 334.696 Z" fill="url(%23lTyCGrzzP-2309410982-linear-gradient)" height="704.2427839655832px" id="lTyCGrzzP" transform="translate(58.388 199.526)" width="414.49961191971533px"/></g></g></svg>)
The form has three sections. One of them is reliably filled with a census entry.
Social:Lives with mother and two siblings. Employed part-time.
Nothing in that changes a treatment plan. It was collected, not assessed, and it is the most common failure in the whole document.
Here is the blank template, a social section that actually asks something, the formulation block that turns three lists into reasoning, and two worked intakes.
Key Takeaway: A biopsychosocial assessment is a structured intake that records the biological, psychological and social factors contributing to a person's presentation, then pulls them into a formulation that explains why this person presented now. In practice the social section is the one that collapses. A commentary in the Journal of the Canadian Academy of Child and Adolescent Psychiatrytitled "Biopsychosocial Assessment: Why the Biopsycho and Rarely the Social?" argues that attempts to apply the model "have continued to neglect a broader conceptualization of what 'social' actual represents," and are "often restricted to collecting information on family composition, child and adolescent school performance, income" [1]. The fix is to write that section against the five domains of social determinants of health defined by Healthy People 2030: economic stability, education access and quality, health care access and quality, neighborhood and built environment, and social and community context [2]. Sully.ai's AI Scribe captures what the client says across all three domains during the intake and writes it into the note.
What a Biopsychosocial Assessment Covers
Three domains, collected in one sitting, usually at the first visit. The assessment establishes the picture the treatment plan is built on.
The Three Domains and What Belongs in Each
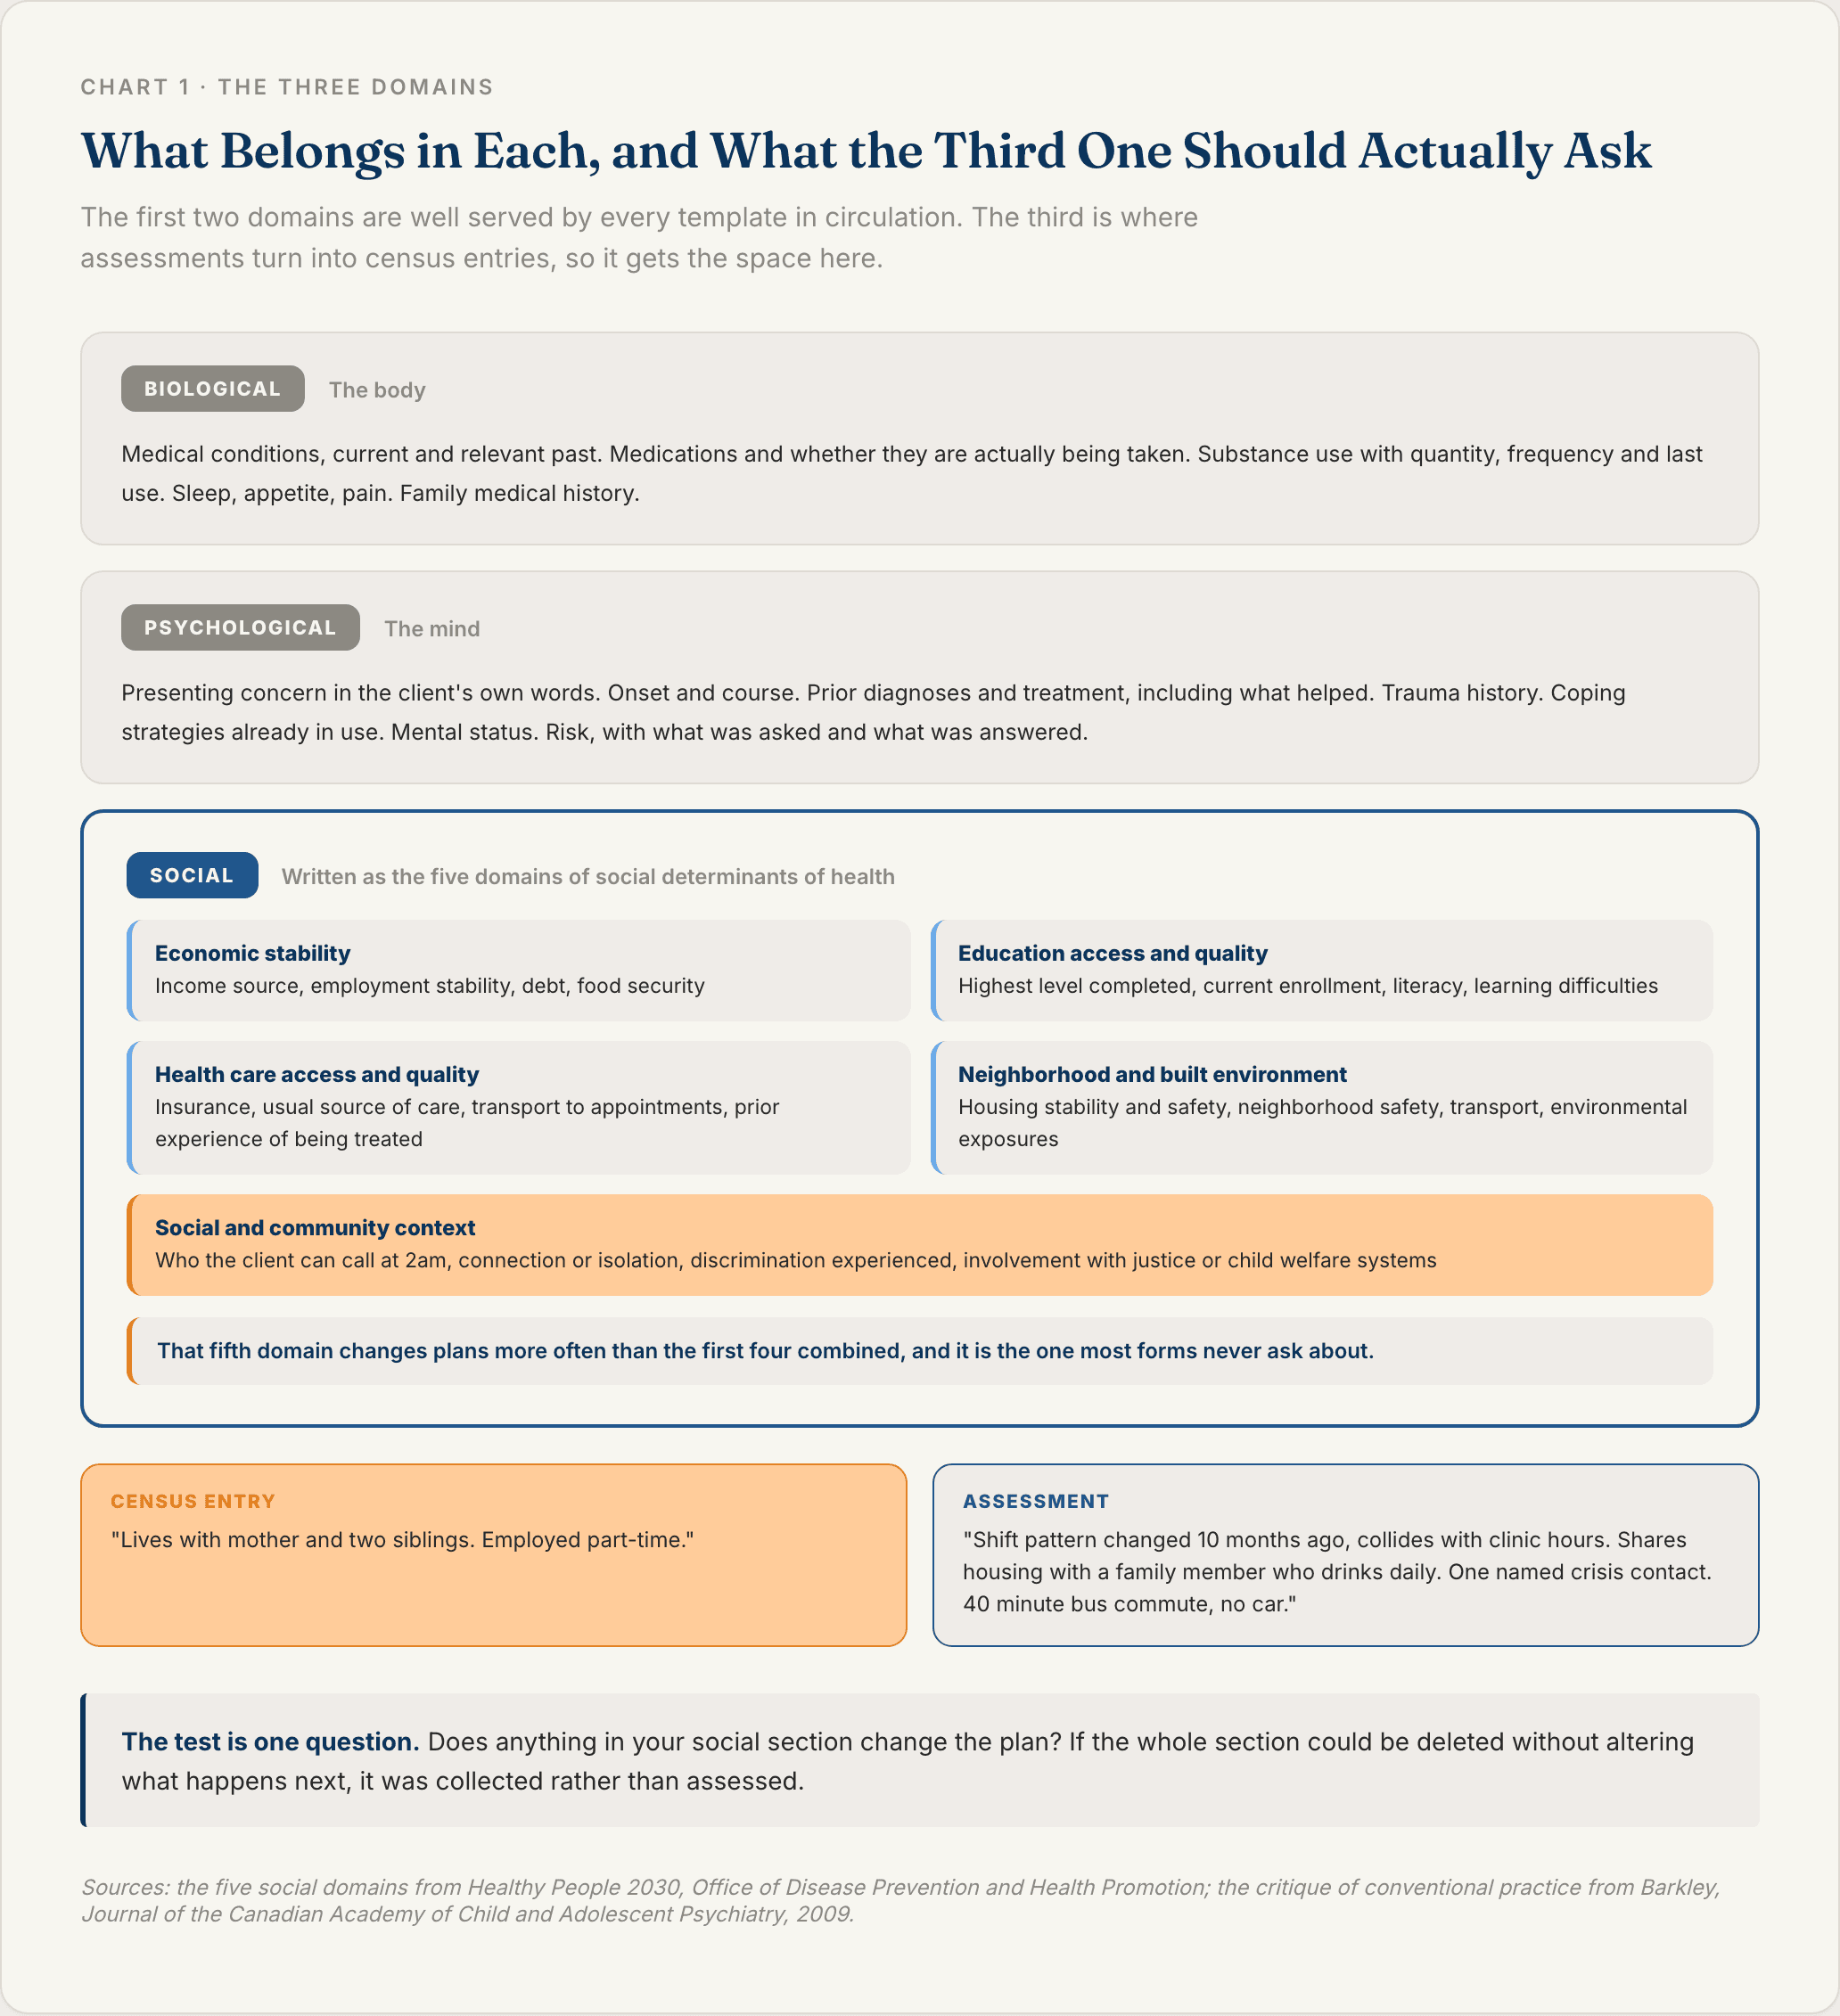
Biological is the body. Medical conditions, medications and whether they are being taken, substance use with quantity and frequency, sleep, appetite, pain, family medical history.
Psychological is the mind. The presenting concern in the client's own words, onset and course, prior diagnoses and treatment, trauma history, coping strategies, mental status, risk.
Social is everything else, and "everything else" is where it goes wrong. Done properly it covers the conditions Healthy People 2030 calls social determinants of health, the circumstances in which people "are born, live, learn, work, play, worship, and age" [2].
Why the Social Section Collapses
This is the part no template guide will tell you, and it is not a matter of opinion.
Jacqueline Barkley, a clinical social worker with thirty years in child welfare, crisis assessment and adult psychiatry, wrote a commentary in 2009 whose title is the whole complaint: "Biopsychosocial Assessment: Why the Biopsycho and Rarely the Social?" Her account of what actually happens [1]:
"The attempts I've observed in conventional practice to use a bio-psycho-social model have continued to neglect a broader conceptualization of what 'social' actual represents. Attempts to apply the model are often restricted to collecting information on family composition, child and adolescent school performance, income, and even sometimes exploring the family narrative."
Read that against the social section of almost any intake form in circulation and it describes it exactly.
The field is quietly conceding the point. A 2025 case study in the Journal of Substance Use and Addiction Treatmentproposes a biopsychosocial-structuralformulation, integrating structural vulnerability into what it calls "the classic 4P model of biopsychosocial case formulation" [3]. People add a fourth axis when the third one is not doing its job.
The fix does not require a new model. Healthy People 2030 already groups social determinants into five domains: economic stability, education access and quality, health care access and quality, neighborhood and built environment, and social and community context [2]. Write the social section against those five and it stops being a demographics box.
You do not need a longer form. You need the third section to ask about the five things that predict outcomes, instead of asking who lives in the house.
Assessment Versus Formulation
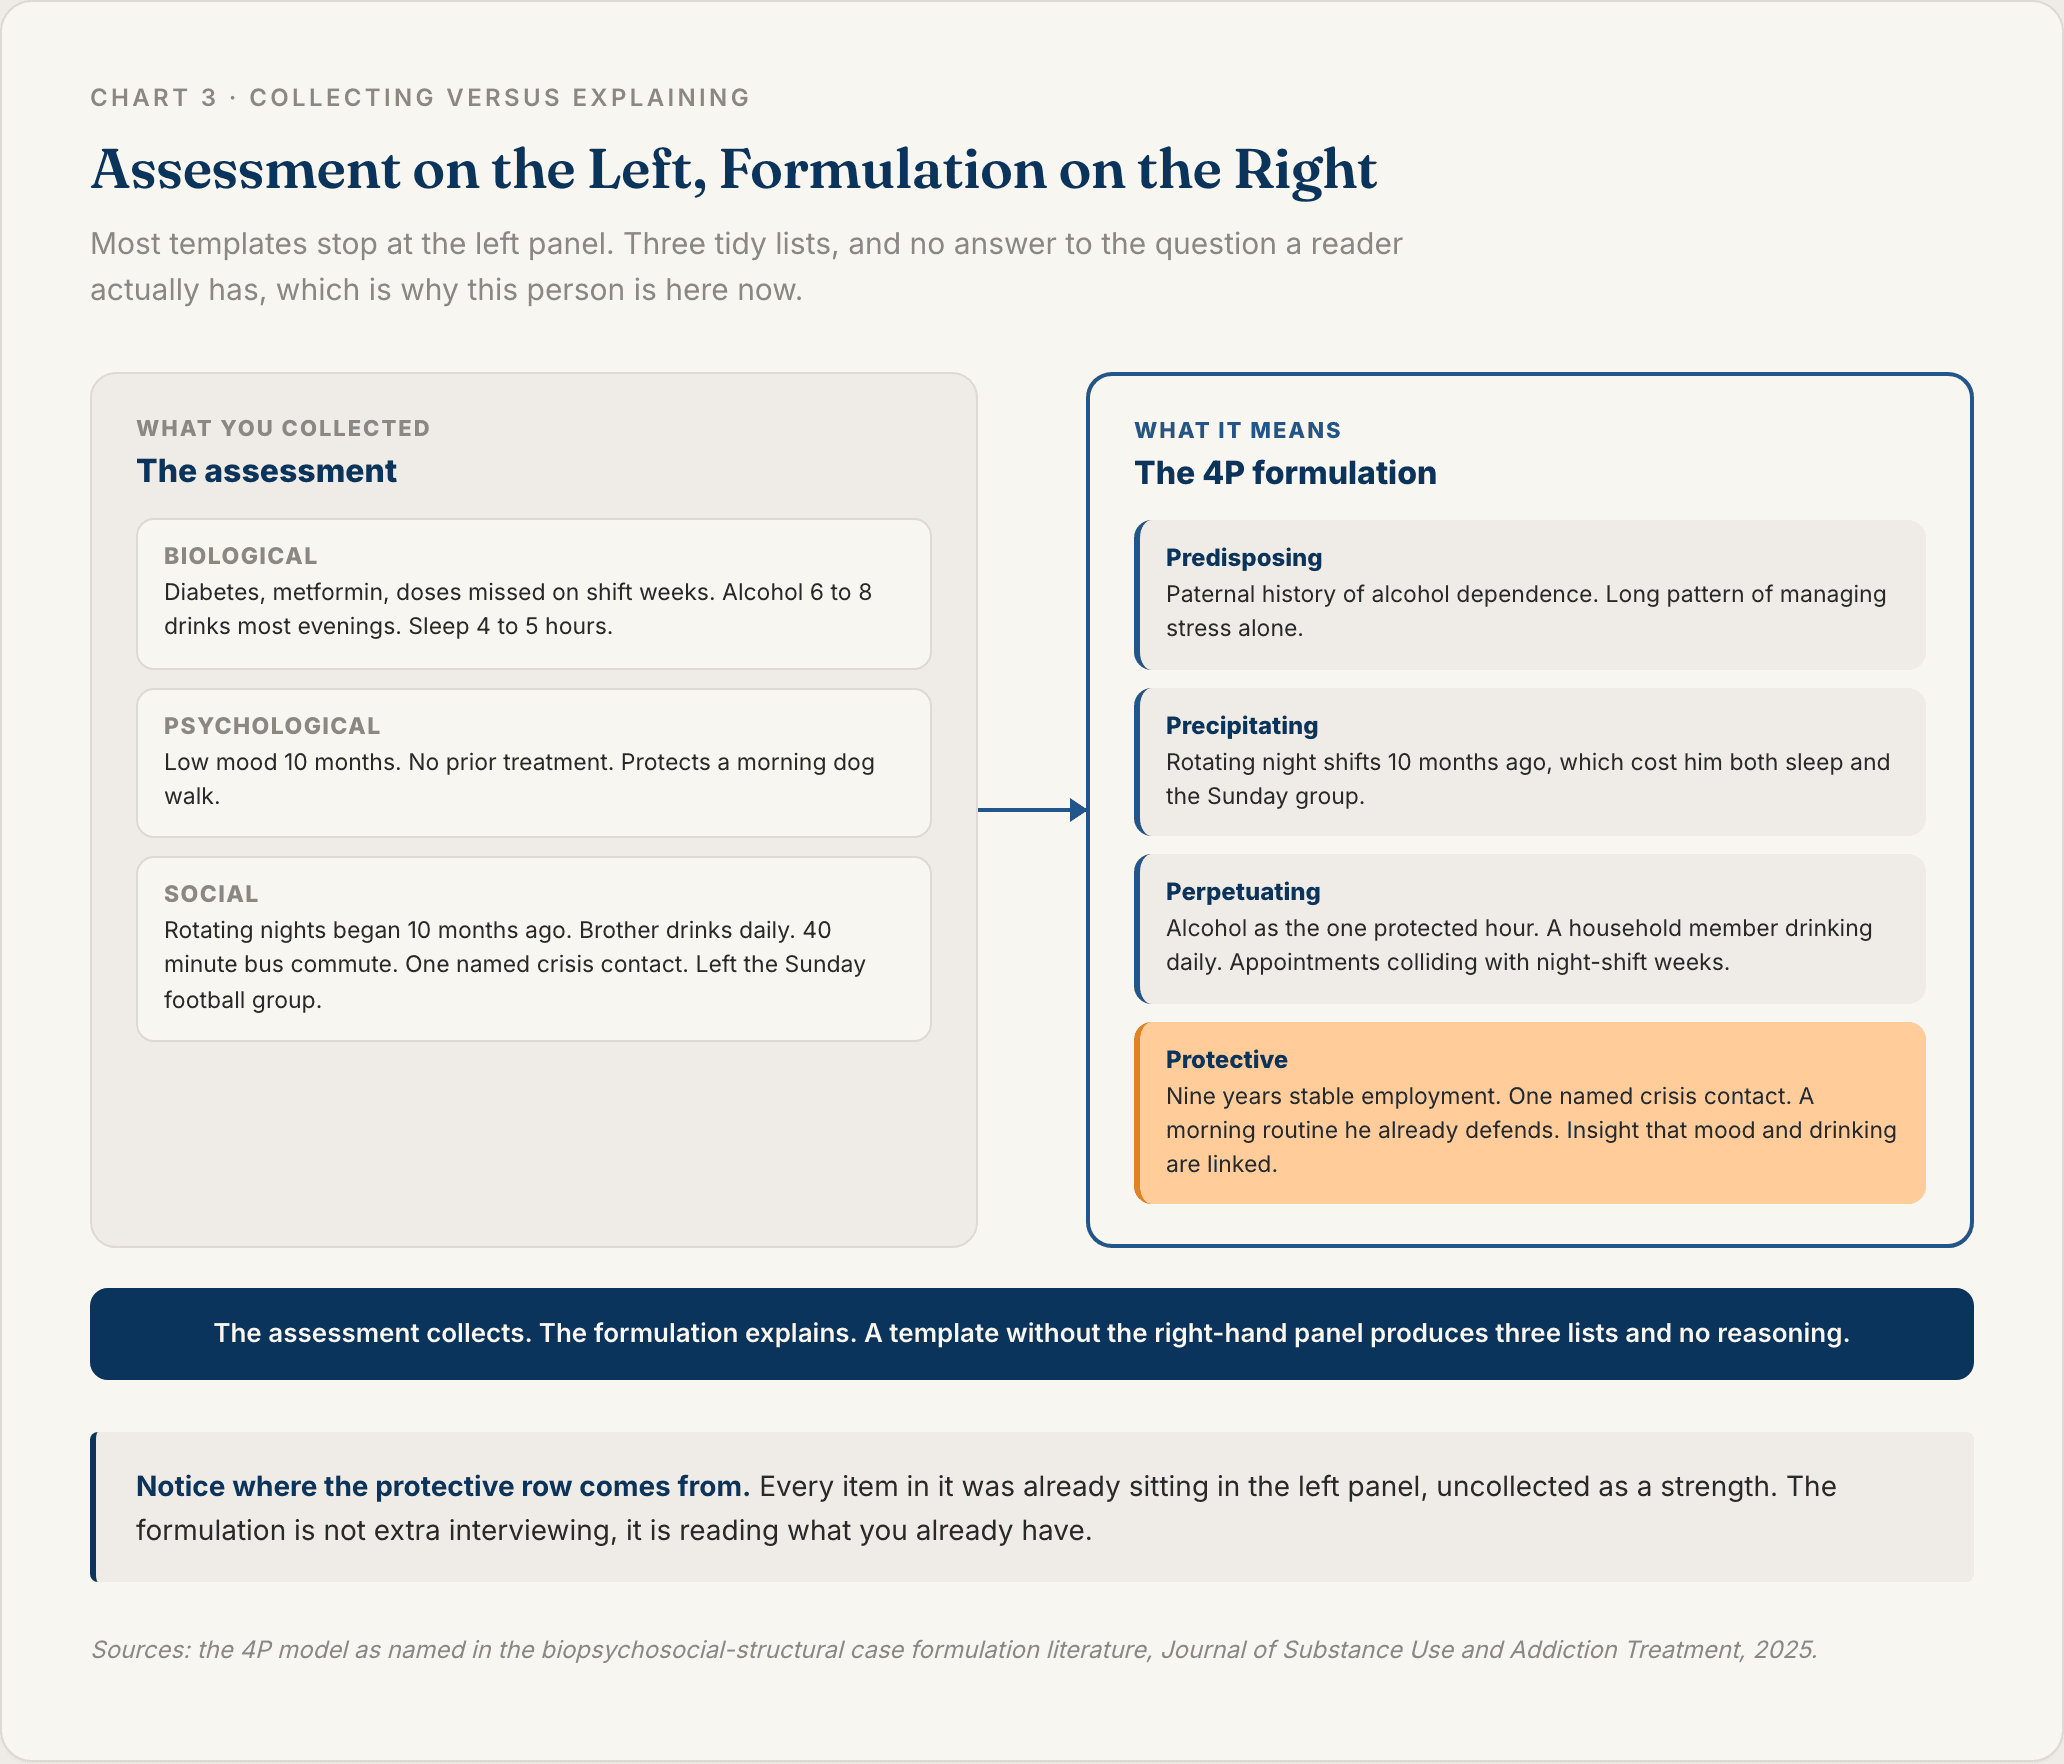
The assessment collects. The formulation explains.
A template with only the first half produces three tidy lists and no reasoning, so a reader cannot tell why this person presented now rather than last year. The formulation is where the three domains stop being parallel and start interacting.
The standard structure is the 4P model, named in the literature as predisposing, precipitating, perpetuating and protective factors [3].
Predisposing: what made this person vulnerable in the first place
Precipitating: what triggered this episode, now
Perpetuating: what is keeping it going
Protective: the strengths and supports a plan can be built on
Searches often ask about the "5 Ps," which adds the presenting problem as a fifth. Both are the same framework. The difference is whether you count the problem itself as a factor or as the heading above them.
The Biopsychosocial Assessment Template
Copy these. Every field carries a prompt in parentheses, which you delete as you fill it in. The one exception is the presenting concern, where the quotation marks stay, because that field holds the client's words rather than yours.
The Blank Template to Copy
BIOPSYCHOSOCIAL ASSESSMENT
Client, date of birth, date of assessment: (and who else was present)
Referral source and reason: (who referred, and what they are asking for)
Consent and, for minors, custody status: (a full psychiatric intake evaluation carries this too)
BIOLOGICAL
Medical conditions: (current and relevant past)
Medications: (including adherence, and what the client says about side effects)
Substance use: (substance, quantity, frequency, last use, prior treatment)
Sleep, appetite, pain: (hours and pattern, appetite change, pain site and severity)
Family medical history: (including mental health and substance use in the family)
PSYCHOLOGICAL
Presenting concern: "(in the client's own words)"
Onset and course: (when it started, what it has done since)
Prior diagnoses and treatment: (what helped, what did not)
Trauma history: (only to the depth the client is ready for at intake)
Coping strategies: (what they already do that works)
Mental status: (summary, or attach the full mental status exam)
Risk: (what you asked, and what the client answered)
SOCIAL
Economic stability: (income source, employment stability, debt, food security)
Education access and quality: (highest level completed, current enrollment, literacy)
Health care access and quality: (insurance, usual source of care, transport to appointments)
Neighborhood and built environment: (housing stability and safety, neighborhood safety, transport)
Social and community context: (who the client can call at 2am, isolation, discrimination, system involvement)
FORMULATION
Predisposing: (what made this person vulnerable)
Precipitating: (what triggered this episode now)
Perpetuating: (what is keeping it going)
Protective: (strengths, supports, and what is already working)
Plan and next appointment: (what happens next, by when, and who is responsible)
Clinician signature and credentials: (and supervising clinician where required)
The Social Section, Written as Five Domains
This is the block that makes the difference. Each domain, with the question that gets you something usable [2].
Economic stability:(income source, employment stability, debt, food security)
Education access and quality:(highest level completed, current enrollment, literacy, learning difficulties)
Health care access and quality:(insurance, usual source of care, transport to appointments, prior experience of being treated)
Neighborhood and built environment: (housing stability and safety, neighborhood safety, transport, environmental exposures)
Social and community context:(who the client can call at 2am, connection or isolation, discrimination experienced, involvement with systems such as justice or child welfare)
That last question changes plans more often than the first four combined, and it is the one most forms never ask.
The Formulation Block
Four rows. Four sentences is enough.
Predisposing: (what made this person vulnerable)
Precipitating: (what triggered this episode now)
Perpetuating: (what is keeping it going)
Protective:(strengths, supports, and what is already working)
The protective row is the one clinicians skip, and it is the row a treatment plan is built on. A formulation with three factors and a blank fourth gives you a problem description with nothing to act on.
Where Sully.ai Fits in Intake Documentation
A full biopsychosocial intake is sixty to ninety minutes of conversation compressed into a form.
The parts that survive that compression are the parts with tick boxes. The social section has the fewest tick boxes and the most narrative, which is precisely why it thins out by the time the note gets typed at seven in the evening. What the client said about the bus route, about the person they can call, about why they stopped the last medication, all of it flattens into a line.
Sully.ai's AI Scribe captures what is said across the whole psychiatry and behavioral healthintake and writes it into the structure the clinician has saved, so those answers survive into the note instead of being summarized away. It runs on a single integration across Epic, Cerner, Meditech and Athenahealth.
Now the boundary, and there is a good study for it rather than a vendor hedge.
A 2026 paper in Behavioral Sciences tested large language models assisting novice counselors with case formulation. AI assistance "significantly enhances the comprehensiveness and coherence of case formulation, while its effects on complexity and specificity are not statistically significant" [4].
Read that carefully, because it is the honest answer to what a scribe does here. AI helped cover the ground and organize it. It did not make the formulation deeper or more specific.
Which is the same point this page has been making. Depth in the social section is a function of what you asked in the room. A scribe protects the answers you got. It does not ask the questions for you.
Sully operates across 5,000+ providers, has delivered 50M+ hours of AI work, and prices each AI role 80 to 90 percent below the human equivalent [5].
Biopsychosocial Assessment Examples Written Out
Two intakes. Both have a social section with real content in it, because that is the entire argument.
An Adult Outpatient Intake
42 year old, referred by primary care for low mood and alcohol use.
BIOLOGICAL: Type 2 diabetes, diagnosed 4 years ago, on metformin 1000 mg twice daily. Reports missing doses "maybe twice a week, when the shifts flip." Hypertension on lisinopril. Alcohol: 6 to 8 standard drinks most evenings, daily for the past 8 months, first drink usually within an hour of getting home. No prior detox, no withdrawal seizures. Sleep 4 to 5 hours, fragmented, worse on night-shift weeks. Appetite reduced. Father had alcohol dependence.
PSYCHOLOGICAL: Presenting concern in his words: "I'm flat all the time and I know the drinking is doing it, but it's the only hour of the day that's mine." Low mood approximately 10 months, following a shift to rotating nights. No prior mental health treatment. Denies suicidal ideation on direct questioning, no plan, no intent, no access concerns. Coping: walks the dog most mornings, describes this as the part of the day he protects.
SOCIAL:
Economic stability: Warehouse supervisor, 9 years, stable employment but rotating shift pattern changed 10 months ago. Income adequate. No food insecurity.
Education access and quality: Completed secondary, trade certification. No literacy concerns.
Health care access and quality: Insured through employer. Primary care attached. Reports missing two of the last four appointments because they fell on night-shift weeks.
Neighborhood and built environment: Stable housing, shares with a brother who also drinks daily. 40 minute bus commute to this clinic, no car.
Social and community context: Names one friend he would call in a crisis. Has withdrawn from a Sunday football group since the shift change. No involvement with justice or child welfare systems.
FORMULATION:
Predisposing: Paternal history of alcohol dependence. Long-standing pattern of managing stress alone.
Precipitating: Rotating night shifts beginning 10 months ago, which disrupted sleep and removed the Sunday football group.
Perpetuating: Alcohol used as the one reliably protected hour. Household member drinking daily. Appointment times colliding with night-shift weeks, so care keeps getting missed.
Protective: Nine years of stable employment. One named crisis contact. A morning routine he already protects. Insight that the drinking and the mood are connected.
Notice what the social section did. It produced three plan items the psychological section never would have: schedule appointments against the shift rota, address the household drinking as a perpetuating factor rather than a detail, and rebuild the Sunday group as a protective one.
An Adolescent Intake
15 year old, school refusal for 6 weeks, referred by the school counselor.
Consent and custody:Mother holds sole legal custody, consent obtained and documented. Client assented and was seen alone for part of the session.
BIOLOGICAL: No chronic conditions, no regular medications. Reports headaches on school mornings, resolving by midday. Sleep onset around 2am, waking 11am on non-school days. No substance use reported.
PSYCHOLOGICAL: In her words: "I can get to the gate and then I just can't." Onset 6 weeks ago, after a friendship group changed. No prior treatment. Denies suicidal ideation on direct questioning. Collateral from mother, who reports the client was previously "the one who got everyone out of the house in the morning."
SOCIAL:
Economic stability: Mother works two part-time jobs. Household receives free school meals.
Education access and quality: Year 10, previously strong attendance. School has offered a phased return but no key adult assigned.
Health care access and quality: Registered with primary care. Mother's work hours make weekday appointments difficult.
Neighborhood and built environment: Stable housing. Walks to school, route passes the home of a member of the former friendship group.
Social and community context: Close to an older cousin, in daily contact. No longer in contact with the previous friendship group. No system involvement.
FORMULATION:
Predisposing: High self-imposed expectations around school performance and attendance.
Precipitating:Friendship group change 6 weeks ago.
Perpetuating: Walking route passing the former friend's home. Sleep phase now shifted by several hours. No assigned key adult at school, so each morning is negotiated from scratch.
Protective: Daily contact with a supportive cousin. School willing to offer a phased return. Strong prior attendance record.
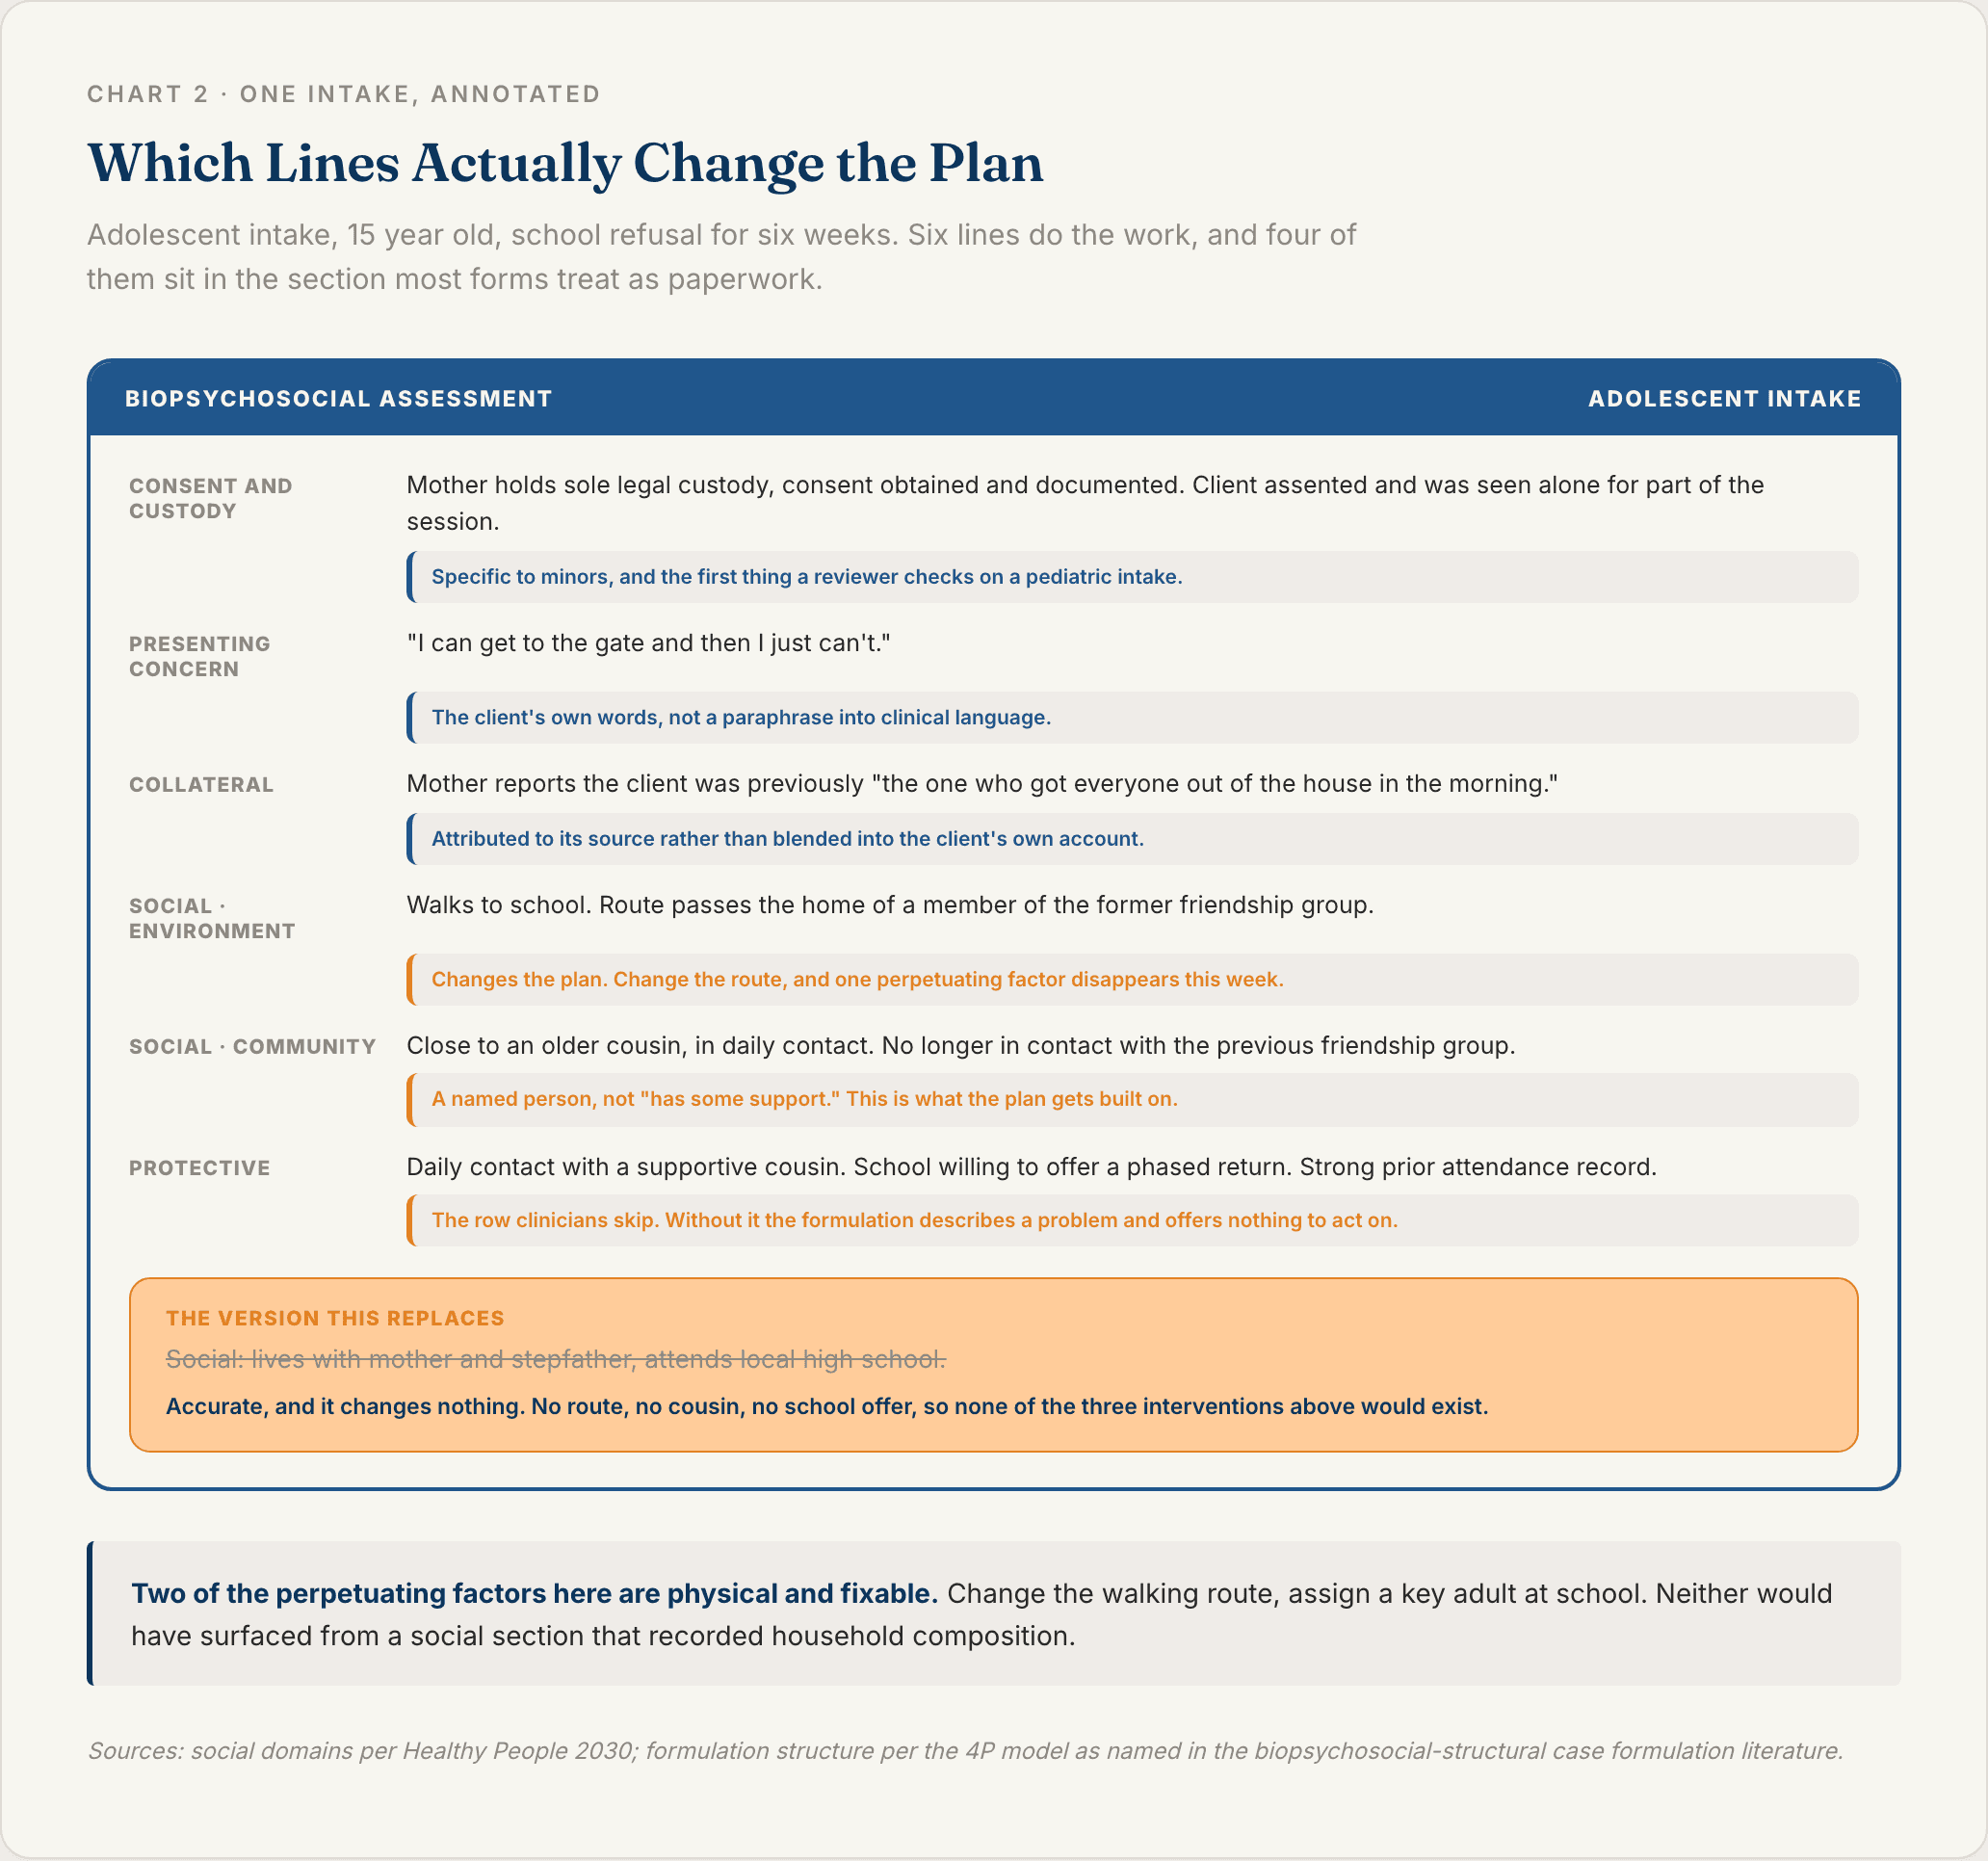
Two of those perpetuating factors are physical and fixable. Change the route, assign a key adult. Neither would have appeared in a social section that recorded "lives with mother, attends local high school."
What Makes an Intake Get Returned
Three Lists and No Formulation
Pages of collected fact with nothing explaining how they connect.
The reader gets to the end knowing a great deal about the person and nothing about why they are here now. The 4P block fixes it in four sentences, and the framework is in active use in current research, including systematic review work on precipitating and perpetuating factors [6].
A Social Section That Is a Household Roster
"Lives with mother and two siblings. Employed part-time."
That is a census entry. It is exactly the failure Barkley describes, information about composition standing in for an assessment of circumstances [1].
The test is one question: does anything in your social section change the plan? If the whole section could be deleted without altering a single line of what happens next, it was collected, not assessed. Write it against the five domains instead [2].
Book a demo and bring your last three intakes. The question worth asking is whether the social section changed any of the three plans.
FAQ
Q: What is a biopsychosocial assessment? A structured intake that records the biological, psychological and social factors contributing to a person's presentation, then pulls them into a formulation explaining why this person presented now. It is used across mental health, substance use treatment and social work, usually at the first visit, where it establishes the picture the treatment plan is built on.
Q: What are the 5 P's of biopsychosocial assessment? The presenting problem, plus the four factors of the classic case formulation model: predisposing, precipitating, perpetuating and protective [3]. Predisposing factors made the person vulnerable, precipitating factors triggered this episode, perpetuating factors keep it going, and protective factors are the strengths a plan gets built on. Some sources call it the 4P model and treat the presenting problem as the heading rather than a fifth factor.
Q: What goes in the social section of a biopsychosocial assessment? More than household composition, which is where most forms stop [1]. Write it against the five domains of social determinants of health: economic stability, education access and quality, health care access and quality, neighborhood and built environment, and social and community context [2]. The prompt list for each domain is on this page.
Q: How long does a biopsychosocial assessment take? Usually one appointment of sixty to ninety minutes for an adult outpatient intake, though it varies by setting and by whether collateral sources are involved. Time pressure is the usual reason the social section gets compressed, which is the specific problem this page is about.
Q: Do you have a free biopsychosocial assessment template? Yes. The blank template, the five-domain social block and the 4P formulation block are all on this page as copy-paste blocks, with two worked intakes covering an adult and an adolescent. Sully.ai's AI Scribe can also capture the intake conversation and write it into the structure you have saved.
Sources
[1] Journal of the Canadian Academy of Child and Adolescent Psychiatry — Biopsychosocial Assessment: Why the Biopsycho and Rarely the Social? [2] Healthy People 2030, Office of Disease Prevention and Health Promotion — Social Determinants of Health [3] Journal of Substance Use and Addiction Treatment — Living with chronic structural vulnerability, a biopsychosocial-structural formulation [4] Behavioral Sciences — Enhancing Case Formulation Competence in Novice Counselors, a ChatGPT-Assisted Approach Using the 4P Model [5] Sully.ai — The AI Workforce for Healthcare [6] Brain Sciences— Risk, Precipitating, and Perpetuating Factors in Functional Neurological Disorder, a Systematic Review
TABLE OF CONTENTS
Hire your
Medical AI Team
Take a look at our Medical AI Team
AI Receptionist
Manages patient scheduling, communications, and front-desk operations across all channels.
AI Scribe
Documents clinical encounters and maintains accurate EHR/EMR records in real-time.
AI Medical Coder
Assigns and validates medical codes to ensure accurate billing and regulatory compliance.
AI Nurse
Assesses patient urgency and coordinates appropriate care pathways based on clinical needs.