"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="WxV_IOPE7-2309410982-linear-gradient" x1="1" x2="0" y1="0.5951279047551217" y2="0.4048720952448783"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="WwbAIQIz8-2309410982-linear-gradient" x1="0.43478742751482424" x2="0.6358595260107829" y1="0.26" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="ZWsVQcPfn-2309410982-linear-gradient" x1="0.9508213454678907" x2="0.04917865453210929" y1="0" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient><linearGradient id="lTyCGrzzP-2309410982-linear-gradient" x1="0.374937164194436" x2="0.625062835805564" y1="0" y2="1"><stop offset="0" stop-color="rgb(255, 255, 255)"/><stop offset="1" stop-color="rgba(255, 255, 255, 0)"/></linearGradient></defs><g d="M 658.002 1357.705 C 1020.321 1357.705 1314.04 1063.989 1314.04 701.667 C 1314.04 339.347 1020.321 45.626 658.002 45.626 C 295.681 45.626 1.96 339.347 1.96 701.667 L 0 701.667 C 0 338.263 294.598 43.665 658.002 43.665 C 1021.404 43.665 1316 338.263 1316 701.667 C 1316 1065.072 1021.404 1359.672 658.002 1359.672 C 294.598 1359.672 0 1065.072 0 701.667 L 1.96 701.667 C 1.96 1063.989 295.681 1357.705 658.002 1357.705 Z M 658.005 1265.053 C 969.154 1265.053 1221.392 1012.819 1221.392 701.667 C 1221.392 390.517 969.154 138.281 658.005 138.281 C 346.856 138.281 94.619 390.517 94.619 701.667 L 92.659 701.667 C 92.659 389.433 345.77 136.321 658.005 136.321 C 970.241 136.321 1223.352 389.433 1223.352 701.667 C 1223.352 1013.902 970.241 1267.017 658.005 1267.017 C 345.77 1267.017 92.659 1013.902 92.659 701.667 L 94.619 701.667 C 94.619 1012.819 346.856 1265.053 658.005 1265.053 Z M 658.002 1166.116 C 914.513 1166.116 1122.452 958.178 1122.452 701.667 C 1122.452 445.16 914.513 237.22 658.002 237.22 C 401.494 237.22 193.551 445.16 193.551 701.667 L 191.59 701.667 C 191.59 444.077 400.411 235.255 658.002 235.255 C 915.596 235.255 1124.412 444.077 1124.412 701.667 C 1124.412 959.261 915.596 1168.084 658.002 1168.084 C 400.411 1168.084 191.59 959.261 191.59 701.667 L 193.551 701.667 C 193.551 958.178 401.494 1166.116 658.002 1166.116 Z M 281.657 818.28 C 298.572 818.28 314.804 825.001 326.765 836.965 L 458.99 969.182 C 470.582 980.781 486.308 987.298 502.706 987.298 L 612.137 987.298 C 646.284 987.298 673.972 959.61 673.972 925.463 L 673.972 891.504 L 675.939 891.504 L 675.939 925.463 C 675.939 960.7 647.374 989.258 612.137 989.258 L 502.706 989.258 C 485.788 989.258 469.562 982.537 457.599 970.573 L 325.378 838.356 C 313.785 826.757 298.056 820.242 281.657 820.244 L 1.173 820.244 L 1.173 818.28 Z M 746.64 888.714 L 1053.046 888.714 C 1069.967 888.714 1086.194 895.435 1098.16 907.398 L 1259.381 1068.619 L 1257.99 1070.007 L 1096.772 908.79 C 1085.175 897.193 1069.446 890.679 1053.046 890.681 L 746.64 890.681 C 729.724 890.681 713.493 883.957 701.533 871.993 L 685.377 855.845 L 686.769 854.453 L 702.917 870.605 C 714.513 882.201 730.241 888.715 746.64 888.714 Z M 667.685 552 L 512.316 396.894 C 494.66 379.264 484.741 355.356 484.739 330.426 L 484.739 0 L 487.632 0 L 487.632 330.426 C 487.632 354.592 497.248 377.763 514.369 394.851 L 669.739 549.957 Z M 782.851 700.491 C 816.998 700.491 844.686 672.804 844.686 638.655 L 844.686 516.468 C 844.687 499.547 851.409 483.32 863.374 471.355 L 1177.508 157.22 L 1178.896 158.607 L 864.762 472.742 C 853.162 484.337 846.646 500.067 846.646 516.468 L 846.646 638.655 C 846.646 673.89 818.088 702.455 782.851 702.455 L 700.405 702.455 L 700.405 700.491 Z M 130.338 534.223 L 213.07 534.223 C 256.112 534.223 291.003 569.114 291.003 612.156 L 291.003 694.888 C 291.003 711.29 297.514 727.017 309.113 738.611 L 472.887 902.378 L 471.496 903.769 L 307.726 739.995 C 295.761 728.033 289.038 711.807 289.038 694.888 L 289.038 612.156 C 289.038 570.198 255.028 536.188 213.07 536.188 L 130.338 536.188 C 113.419 536.187 97.193 529.465 85.23 517.5 L 77.071 509.345 C 65.107 497.381 58.386 481.153 58.388 464.233 L 58.388 199.526 L 60.348 199.526 L 60.348 464.233 C 60.349 480.631 66.863 496.358 78.458 507.954 L 86.617 516.113 C 98.213 527.709 113.94 534.223 130.338 534.223 Z" fill="transparent" height="1359.6717183844698px" id="DcyumyANr" transform="translate(0 -43.665)" width="1316px"><g opacity="0.5"><path d="M 658.002 1314.039 C 1020.321 1314.039 1314.04 1020.324 1314.04 658.001 C 1314.04 295.681 1020.321 1.961 658.002 1.961 C 295.681 1.961 1.96 295.682 1.96 658.001 L 0 658.001 C 0 294.598 294.598 0 658.002 0 C 1021.404 0 1316 294.598 1316 658.001 C 1316 1021.407 1021.404 1316.007 658.002 1316.007 C 294.598 1316.007 0 1021.407 0 658.001 L 1.96 658.001 C 1.96 1020.324 295.681 1314.039 658.002 1314.039 Z" fill="rgb(255, 255, 255)" height="1316.0065114752902px" id="dxf13D52Y" transform="translate(0 43.665)" width="1316px"/></g><g opacity="0.3"><path d="M 565.347 1128.732 C 876.496 1128.732 1128.733 876.498 1128.733 565.346 C 1128.733 254.196 876.496 1.961 565.347 1.961 C 254.197 1.961 1.961 254.196 1.961 565.346 L 0 565.346 C 0 253.112 253.111 0 565.347 0 C 877.582 0 1130.693 253.112 1130.693 565.346 C 1130.693 877.581 877.582 1130.696 565.347 1130.696 C 253.111 1130.696 0 877.581 0 565.346 L 1.961 565.346 C 1.961 876.498 254.197 1128.732 565.347 1128.732 Z" fill="rgb(255, 255, 255)" height="1130.6960934794101px" id="if1BmYw1S" transform="translate(92.659 136.321)" width="1130.693351805604px"/></g><g opacity="0.15"><path d="M 466.412 930.861 C 722.923 930.861 930.862 722.922 930.862 466.411 C 930.862 209.905 722.923 1.965 466.412 1.965 C 209.904 1.965 1.961 209.905 1.961 466.411 L 0 466.411 C 0 208.822 208.821 0 466.412 0 C 724.006 0 932.822 208.822 932.822 466.411 C 932.822 724.005 724.006 932.828 466.412 932.828 C 208.821 932.828 0 724.005 0 466.411 L 1.961 466.411 C 1.961 722.922 209.904 930.861 466.412 930.861 Z" fill="rgb(255, 255, 255)" height="932.8284667407987px" id="ef75NsYf6" transform="translate(191.59 235.255)" width="932.8219552655086px"/></g><g opacity="0.5"><path d="M 280.484 0 C 297.399 0 313.63 6.721 325.592 18.685 L 457.817 150.902 C 469.408 162.501 485.135 169.018 501.533 169.017 L 610.964 169.017 C 645.111 169.017 672.799 141.33 672.799 107.182 L 672.799 73.223 L 674.766 73.223 L 674.766 107.182 C 674.766 142.42 646.201 170.978 610.964 170.978 L 501.533 170.978 C 484.614 170.978 468.389 164.257 456.426 152.293 L 324.205 20.076 C 312.611 8.477 296.883 1.961 280.484 1.964 L 0 1.964 L 0 0 Z" fill="url(%23cQ4xRdUtr-2309410982-linear-gradient)" height="170.97763275969464px" id="cQ4xRdUtr" transform="translate(1.173 818.28)" width="674.7656780356198px"/></g><g opacity="0.5"><path d="M 61.263 34.261 L 367.669 34.261 C 384.589 34.261 400.817 40.982 412.783 52.945 L 574.004 214.166 L 572.612 215.554 L 411.395 54.337 C 399.798 42.74 384.069 36.226 367.669 36.228 L 61.263 36.228 C 44.347 36.228 28.116 29.504 16.155 17.54 L 0 1.391 L 1.391 0 L 17.54 16.152 C 29.136 27.747 44.864 34.261 61.263 34.261 Z" fill="url(%23WxV_IOPE7-2309410982-linear-gradient)" height="215.55382175474415px" id="WxV_IOPE7" transform="translate(685.377 854.453)" width="574.0036823012563px"/></g><g opacity="0.5"><path d="M 182.946 552 L 27.577 396.894 C 9.921 379.264 0.002 355.356 0 330.426 L 0 0 L 2.893 0 L 2.893 330.426 C 2.893 354.592 12.509 377.763 29.63 394.851 L 185 549.957 Z" fill="url(%23WwbAIQIz8-2309410982-linear-gradient)" height="552px" id="WwbAIQIz8" transform="translate(484.739 0)" width="185px"/></g><g opacity="0.5"><path d="M 82.446 543.271 C 116.593 543.271 144.281 515.583 144.281 481.435 L 144.281 359.248 C 144.282 342.327 151.004 326.1 162.969 314.135 L 477.103 0 L 478.491 1.387 L 164.356 315.522 C 152.757 327.117 146.241 342.846 146.241 359.248 L 146.241 481.435 C 146.241 516.67 117.683 545.235 82.446 545.235 L 0 545.235 L 0 543.271 Z" fill="url(%23ZWsVQcPfn-2309410982-linear-gradient)" height="545.2346136318063px" id="ZWsVQcPfn" transform="translate(700.405 157.22)" width="478.4906210693257px"/></g><g opacity="0.5"><path d="M 71.95 334.696 L 154.682 334.696 C 197.724 334.696 232.616 369.588 232.616 412.63 L 232.616 495.362 C 232.616 511.764 239.126 527.491 250.725 539.084 L 414.5 702.851 L 413.108 704.243 L 249.338 540.469 C 237.373 528.507 230.651 512.281 230.651 495.362 L 230.651 412.63 C 230.651 370.672 196.64 336.661 154.682 336.661 L 71.95 336.661 C 55.031 336.661 38.805 329.939 26.843 317.974 L 18.683 309.819 C 6.719 297.854 -0.001 281.627 0 264.707 L 0 0 L 1.961 0 L 1.961 264.707 C 1.961 281.105 8.475 296.832 20.07 308.428 L 28.229 316.587 C 39.825 328.182 55.552 334.697 71.95 334.696 Z" fill="url(%23lTyCGrzzP-2309410982-linear-gradient)" height="704.2427839655832px" id="lTyCGrzzP" transform="translate(58.388 199.526)" width="414.49961191971533px"/></g></g></svg>)
DAP is faster than SOAP because it has three fields instead of four. It gets there by merging Subjective and Objective into one Data field.
That merge is the whole pitch. It is also the whole problem, and no guide to DAP mentions it.
Here is the blank template, three worked examples, a direct answer to the DAP versus SOAP question, and the one wording habit that fixes the Data field.
Key Takeaway: A DAP note records a session in three parts. Data is what happened and what was observed. Assessment is the clinician's interpretation. Plan is what happens next. It is a condensed alternative to SOAP, which covers the same ground in four parts by separating Subjective, what the patient reported, from Objective, what the clinician measured or observed [1]. That separation is where DAP gives something up. In SOAP, attribution is structural, because the boxes decide who said what. In DAP both live in one field, so the wording has to carry it. The Assessment also does more than most examples suggest: in psychiatric settings progress notes must contain "recommendations for revisions in the treatment plan as indicated, as well as precise assessment of the patient's progress in accordance with the original or revised treatment plan" [2]. Sully.ai's AI Scribe captures the session and writes it into DAP with the client's own words preserved.
What a DAP Note Is
Three fields, one session, usually under 200 words. It is the format agencies pick when clinicians are writing eight notes a day, and Sully publishes it as a DAP note template.
The Three Fields
Data is what happened in the session. What the client said, what you observed, what was done.
Assessment is your interpretation. Not a summary of the Data, which is the mistake almost every published example makes, but a judgment about what the Data means and where the client is against the plan.
Plan is what happens next. The intervention, the interval, anything the client is doing between sessions.
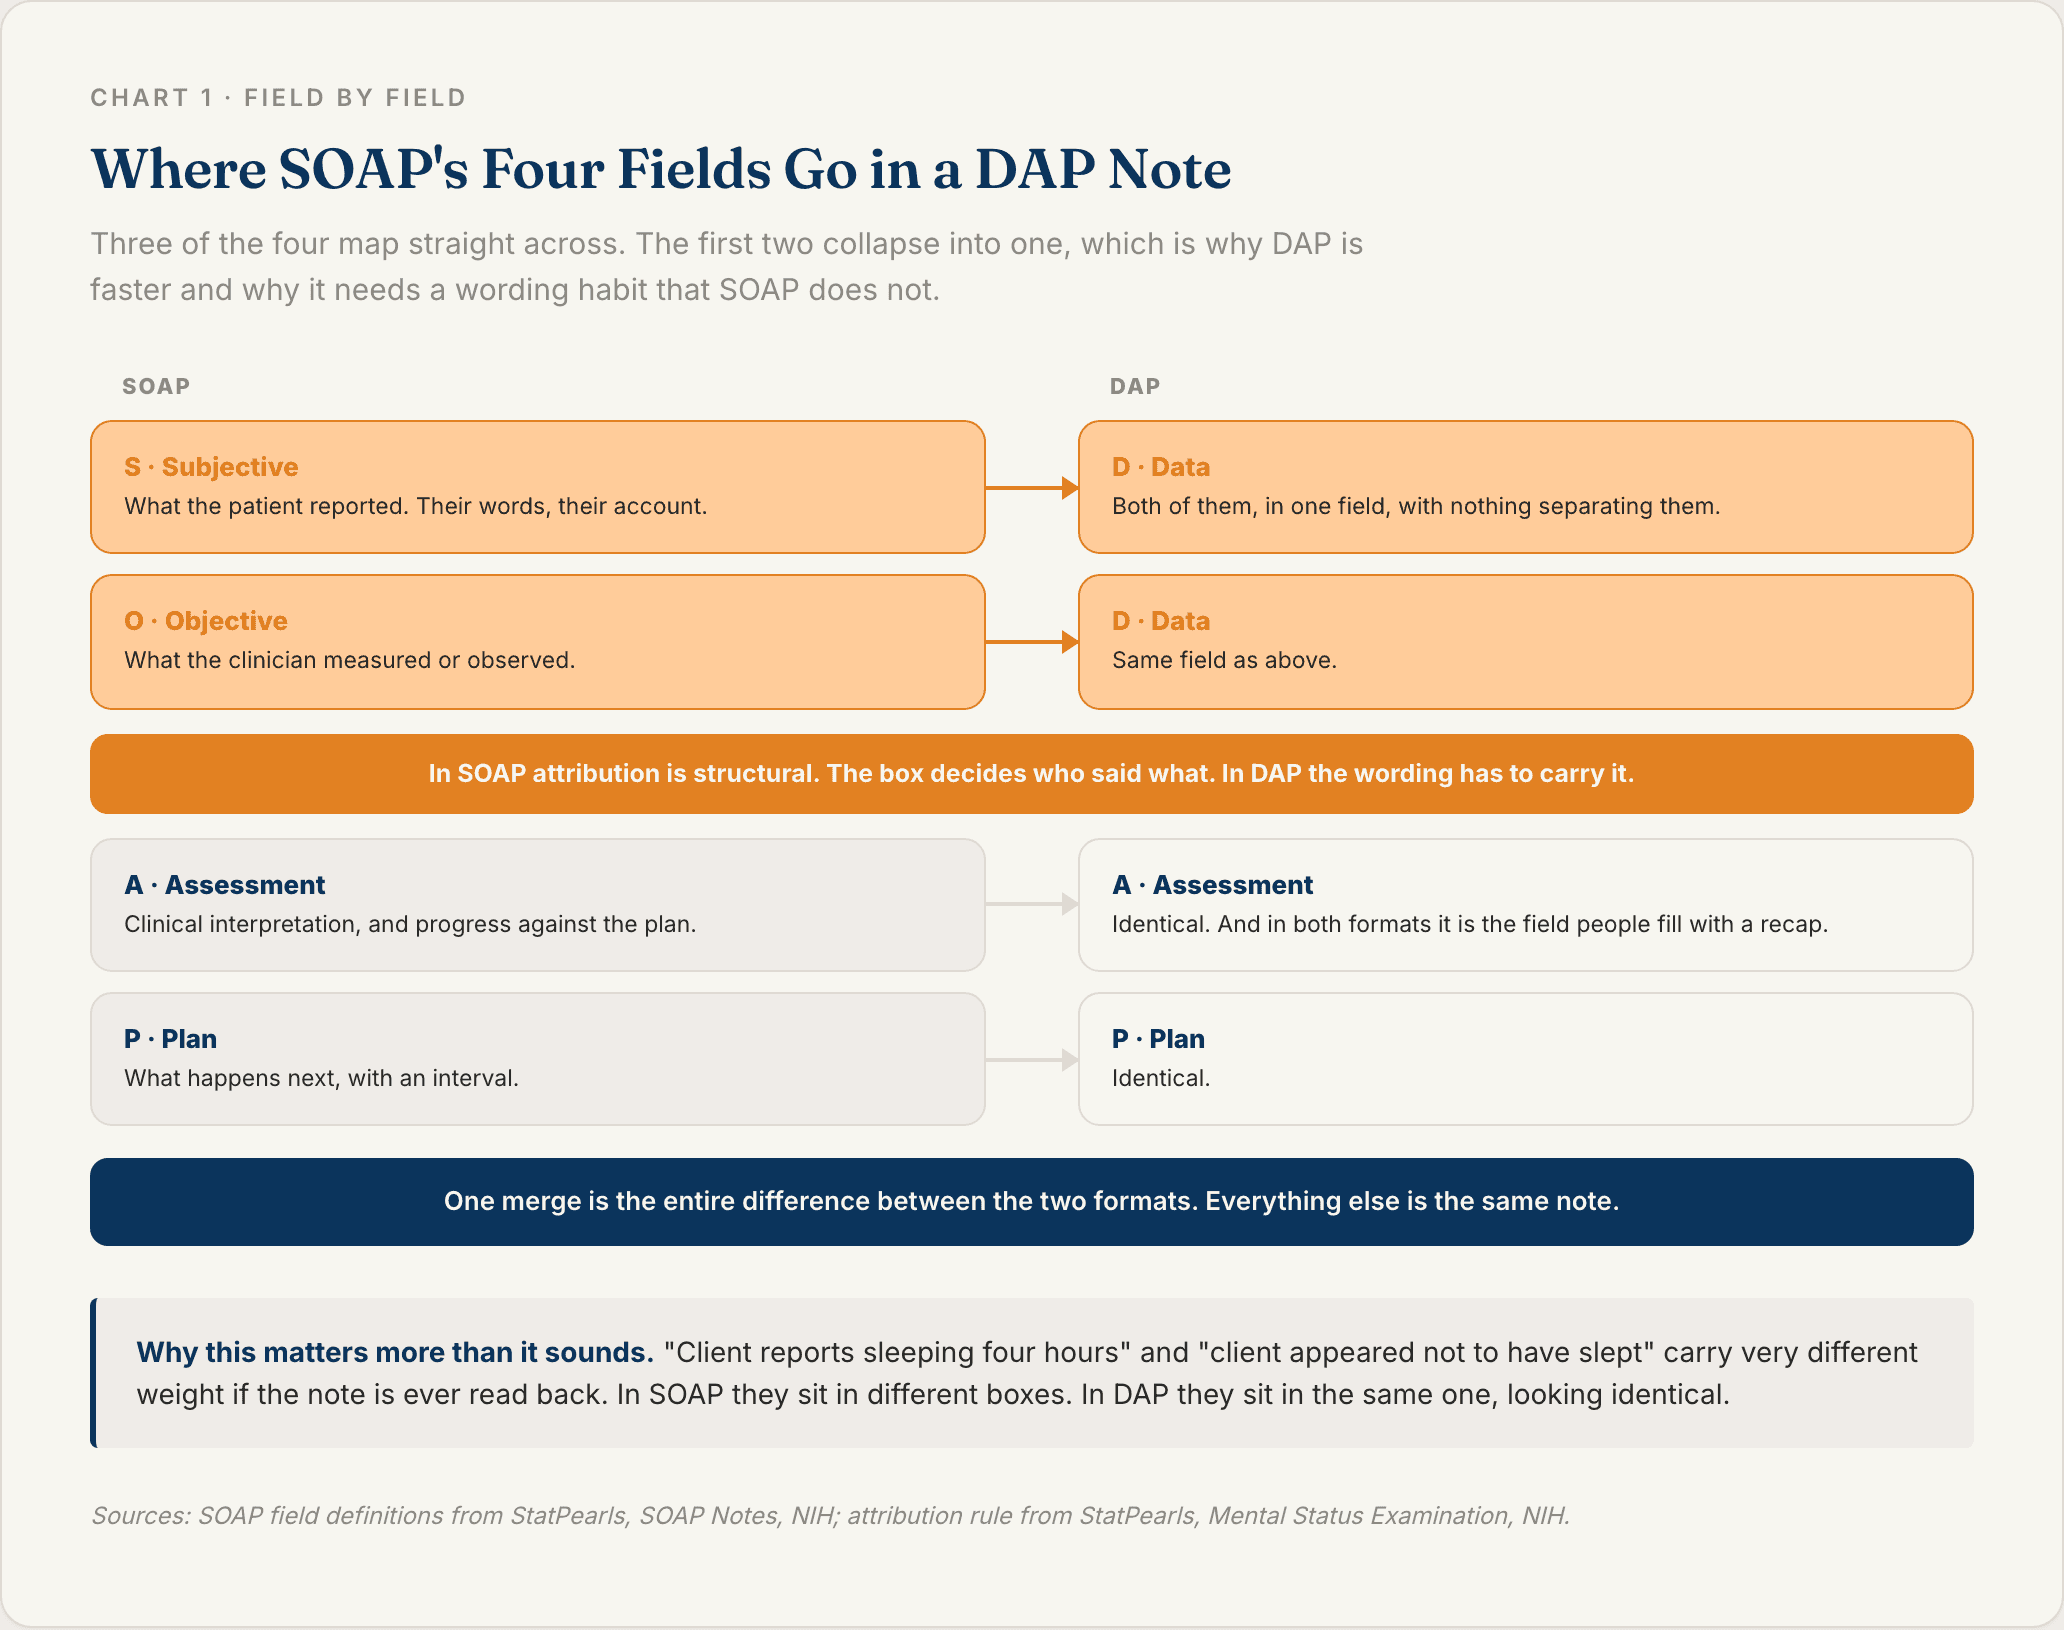
What the Single Data Field Hides
Here is the part no competing page mentions, and it follows directly from the chart above.
In a SOAP note, attribution is structural. The Subjective field holds what the patient reported. The Objective field holds what the clinician measured or observed [1]. You cannot mix them up without putting text in the wrong box, and anyone reading the note can tell at a glance which claims came from whom.
DAP removes that guardrail. One field holds both.
Read these two lines and notice that nothing in the DAP structure tells them apart:
Client reports sleeping four hours a night. Client appeared not to have slept.
The first is a patient report. The second is a clinical observation. They carry completely different weight if anyone ever reads the note back, and in a Data field they sit side by side looking identical.
The fix is a wording habit, not a longer note. Quotation marks for the client's words. Observation verbs for yours.
This is not a new rule. It is the same one that governs the mood and affect fields of a mental status exam, where mood is "documented with quotations transcribing the patient's response verbatim" and affect is "the clinician's interpretation of a patient's observed expression through their non-verbal language" [3]. In an MSE the two have separate boxes. DAP asks you to keep the same discipline with no box to enforce it.
And a second point, about the A. Most DAP examples treat Assessment as a recap of the Data. It is not. In psychiatric settings the progress note has to carry "precise assessment of the patient's progress in accordance with the original or revised treatment plan," plus recommendations for revising that plan [2]. The Assessment is where the session connects to the plan.
A DAP note whose Assessment restates the Data has no assessment in it.
DAP or SOAP
This is the most asked question about the format, so here is the direct answer.
Use DAP when the session turns on one thread and speed matters. It is common in counseling and in behavioral health and substance use work, where a counselor may document many contacts in a day and where federal standards require the frequency of services to be identified on the plan [4].
Use SOAP when the record has to show symptom change over time, or when the subjective and objective split is doing clinical work rather than just taking up space. The SOAP note article covers that format in full.
Neither is more or less compliant.There is no federal rule that names DAP, because DAP is a format rather than a document type. What applies is what applies to any entry in the record: it must be legible, complete, dated, timed, and authenticated by the person responsible for providing or evaluating the service [5]. A DAP note that satisfies those is fine. The three letters are not the requirement.
If you want all three formats compared side by side, including BIRP, that is in the therapy notes article.
The DAP Note Template
One block, complete as written. Paste it straight into a chart.
The Blank Template to Copy
DAP NOTE
Client, date of service:(and who was present)
Start and stop time, duration:(the times the session actually ran)
Modality and CPT code:(individual, group, family, telehealth)
D, DATA
Client reported: "[their words, in quotation marks]"
Observed:(what you saw and heard, describable by a second clinician)
In session:(what was done, and what the client did with it)
A, ASSESSMENT
Interpretation: (what the Data means, not what the Data said)
Progress against plan: (the named goal from the treatment plan, and where the client is on it)
Risk: (what you asked, and what the client answered)
P, PLAN
Next intervention: (what you will do next session)
Between sessions:(anything the client agreed to do)
Interval and next appointment: (how often, and when)
Plan revisions:(any change to the treatment plan, or "none indicated")
Signature and credentials:(the person who provided the service)
The three sub-prompts under D are the point of the whole page. They put back the attribution that the merged field took away.
The Attribution Habit Inside the D
Three ways to write the same underlying content. Only two of them belong in a note.

The rule in one line: in SOAP the box decides, in DAP the verb decides. "Client stated" and "client reported" attribute to them. "Appeared," "presented," "was observed to" attribute to you. A sentence with neither belongs to nobody.
Where Sully.ai Fits in Session Documentation
DAP gets chosen because it is fast, and it still gets written after the session rather than during it.
What disappears first in that gap is the client's exact phrasing, which is the only thing making the Data field's attribution work. "Client reports feeling overwhelmed" is a paraphrase, and it is already halfway to being your words rather than theirs. "It's like the whole week is stacked on a Tuesday" is what they actually said, and it is both better clinical material and better evidence.
Sully.ai's AI Scribe captures what is said during the session and writes it into DAP with the client's own words preserved, so the D keeps its attribution instead of flattening into clinician summary. It runs on a single integration across Epic, Cerner, Meditech and Athenahealth.
Two boundaries worth being specific about.
A scribe is good at the D and has no business writing the A. Data is a recall problem. Assessment is a judgment problem, and the A is the field a reviewer reads to decide whether the session was clinically necessary. Read it before you sign it.
A scribe cannot resolve ambiguous attribution for you. Audio does not always reveal whether "things have been rough at home" was the client's sentence or your summary of several sentences. When it is genuinely ambiguous, that is a clinical call, and the honest answer is that the person who was in the room has to make it.
Sully operates across 5,000+ providers, has delivered 50M+ hours of AI work, and prices each AI role 80 to 90 percent below the human equivalent [6].
DAP Note Examples Written Out
Three settings. Every Data field below demonstrates the attribution habit, because that is the argument.
A Counseling Session
Bereavement counseling, fourth session, 50 minutes, individual.
D, DATA Client reported: "I keep setting two places at the table and then I have to put one away." Reported sleeping five to six hours, up from three to four at intake, and eating "properly, most days now." Denied suicidal ideation on direct questioning, no plan, no intent. Observed: Client wept briefly at minute 12 while describing the table, recovered within two minutes without prompting, and continued the thread unaided. Speech normal rate. Made and held eye contact throughout, which is a change from sessions one and two. In session: Continued grief processing focused on routines rather than on the death itself. Client completed the letter-writing exercise agreed last session and read part of it aloud.
A, ASSESSMENTInterpretation: Grief remains acute but the client is now able to stay with distressing material without avoidance, which she could not do at intake. The recovery within two minutes and the continuation unaided are the markers here, not the crying itself. Progress against plan: Goal one, tolerate grief-related distress without leaving the topic. Met in session for the first time. Risk: Asked directly about thoughts of self-harm. Denies, no plan, no intent, no access concerns raised.
P, PLAN Next intervention: Begin work on the table routine specifically, as a behavioral experiment. Between sessions: Client to keep the letter and add to it if she wishes, no requirement. Interval: Weekly, next appointment 24 September. Plan revisions: None indicated.
Look at the D. Two sentences attributed to her with quotation marks, three attributed to you with observation verbs, and nothing floating in between.
A Substance Use Counseling Session
Opioid treatment program, individual counseling, 30 minutes.
D, DATA Client reported: "I nearly used on Saturday but I called my sister instead." Reported attending all scheduled dosing appointments for the past two weeks. Reported that the vocational appointment "didn't go anywhere" because the office closed early. Observed: Client arrived on time, which is a change from the previous three sessions. Engaged throughout, no drowsiness, no signs of intoxication or withdrawal noted. In session: Reviewed the Saturday episode in detail, including what preceded it and what he did instead. Identified the phone call as a usable strategy rather than a one-off.
A, ASSESSMENTInterpretation: First reported instance of the client interrupting a craving with a planned alternative rather than after the fact. Naming the sister as a specific contact rather than "family" makes this repeatable. Progress against plan: Goal one, attend all dosing appointments for four consecutive weeks. Two of four complete. Goal two, complete two vocational sessions. Not started, blocked by a scheduling failure on the service side rather than by the client. Risk: No suicidal or homicidal ideation. No overdose events reported.
P, PLAN Next intervention: Build the phone-call strategy into a written craving plan with two named contacts. Between sessions: Client to contact the vocational service to rebook; counselor to follow up with that service directly, since the failure was theirs. Interval: Fortnightly counseling, daily observed dosing continuing. Plan revisions: None to the goals. Note added that vocational access is a service-side barrier.
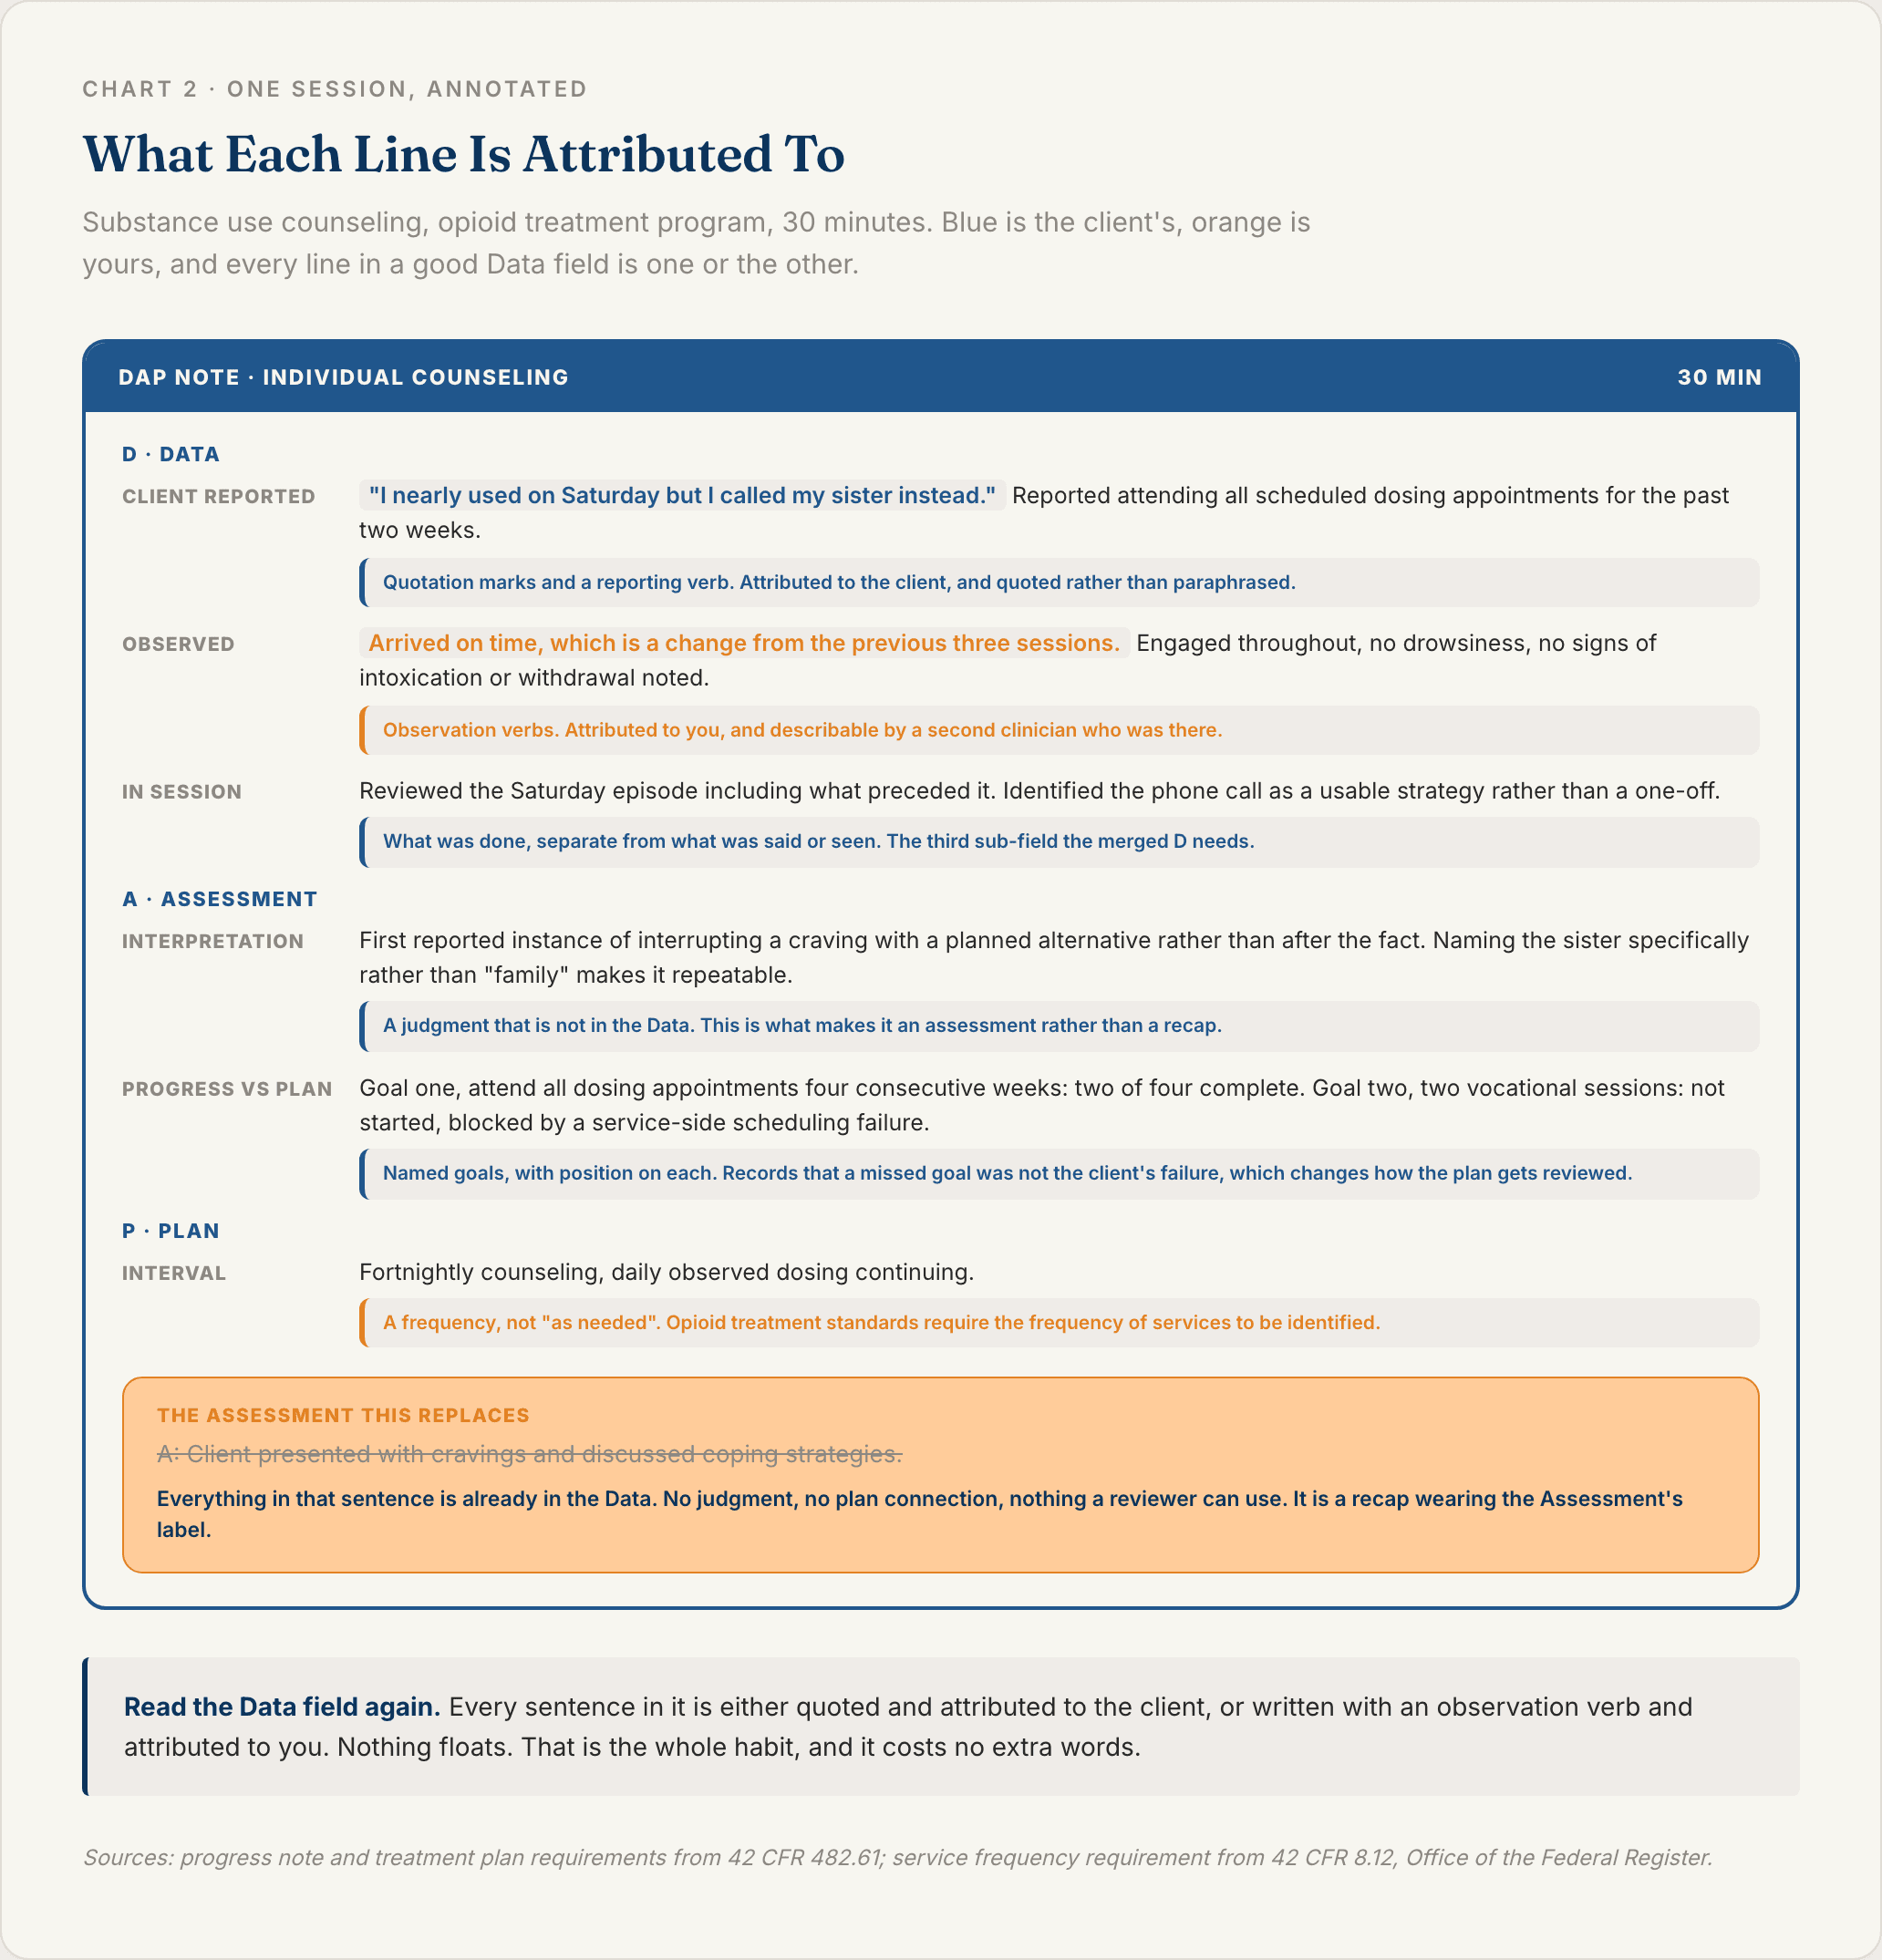
The Assessment here does two things a recap could not. It identifies why this week is different from the previous three, and it records that a missed goal was not the client's failure, which is the kind of detail that changes how a plan gets reviewed. Opioid treatment programs are required to identify the frequency with which services are provided, which is why the Plan carries an interval rather than "as needed" [4].
A Case Management Contact
DAP is not only for therapy hours. Here is a care coordination call, eight lines.
D, DATA Client reported: "The pharmacy said they never got it." Reported he has been without the prescription for four days. Observed: Call lasted 11 minutes. Client sounded frustrated but was engaged and problem-solving. In session: Contacted the prescribing office during the call and confirmed the prescription was sent to the wrong branch.
A, ASSESSMENTInterpretation: Access failure rather than adherence failure. The client took three separate steps to resolve this before contacting me. Progress against plan: Medication adherence goal is unaffected; this is a supply interruption.
P, PLANPrescription redirected to the correct branch, collection confirmed for today. Follow-up call Thursday to confirm collection. No change to the care plan.
Same three fields, an eighth of the length. The attribution habit still applies, and it is what makes "the pharmacy said they never got it" readable as the client's account rather than as established fact.
What Gets a DAP Note Returned
An Assessment That Repeats the Data
This is the failure the format invites, and it is the most common one.
A: Client presented with grief symptoms and discussed her routines at home.
Everything in that sentence is already in the Data. Compare with the version from the first example: the client can now stay with distressing material without avoidance, which she could not do at intake, and the marker is the unaided recovery rather than the crying.
The test is one question: does the Assessment contain a judgment that is not already in the Data? If not, you wrote a summary and labeled it an assessment [2].
A Data Field With No Attribution
Client is overwhelmed by work.
That sentence belongs to nobody. Did the client say it, or did you conclude it? A reader cannot tell, and in a merged field there is no box to fall back on.
Both rewrites are fine. Only the ambiguous version is not:
Client stated, "I can't keep up with any of it."
Client presented as overwhelmed, speaking rapidly and returning to work three times without prompting.
Entries have to be complete and authenticated by the person who provided the service [5], and an unattributed claim makes both of those harder to stand behind [3].
Book a demo and bring five recent DAP notes. The question worth asking is how many Data fields contain a sentence that belongs to nobody.
FAQ
Q: What is the main difference between a DAP note and a SOAP note? SOAP has four fields and separates Subjective, what the patient reports, from Objective, what the clinician measures or observes [1]. DAP has three and merges those into a single Data field. DAP is faster to write, and it gives up the structural guarantee that attribution is preserved, so in a DAP note the wording has to carry it instead.
Q: What is a DAP case note? A DAP note used for case management or care coordination rather than a therapy session. Same three fields, usually much shorter. There is a worked example on this page of a care coordination call written as a DAP note in eight lines.
Q: Can you provide an example of a DAP note? Yes, three of them: a bereavement counseling session, a substance use counseling session in an opioid treatment program, and a case management contact. Each is written out in full with the blank template above it.
Q: What are the requirements for DAP notes? There is no federal rule that names DAP, because DAP is a format rather than a document type. What applies is what applies to any entry in the record. Entries must be legible, complete, dated, timed and authenticated by the person who provided or evaluated the service [5]. In psychiatric settings, progress notes must also carry an assessment of the patient's progress against the treatment plan and any recommended revisions [2]. Those rules bind hospitals and opioid treatment programs directly rather than outpatient private practice, but reviewers in every setting reason from the same expectations.
Q: Do you have a free DAP note template? Yes. The blank template is on this page as a copy-paste block, with the attribution prompts built into the Data field and three worked examples. Sully.ai's AI Scribe can also capture the session and write it into DAP with the client's own words preserved.
Sources
[1] StatPearls, National Center for Biotechnology Information — SOAP Notes [2] Office of the Federal Register — 42 CFR 482.61, Special medical record requirements for psychiatric hospitals [3] StatPearls, National Center for Biotechnology Information — Mental Status Examination [4] Office of the Federal Register — 42 CFR 8.12, Federal opioid treatment standards [5] Office of the Federal Register — 42 CFR 482.24, Condition of participation, Medical records[6] Sully.ai — The AI Workforce for Healthcare
TABLE OF CONTENTS
Hire your
Medical AI Team
Take a look at our Medical AI Team
AI Receptionist
Manages patient scheduling, communications, and front-desk operations across all channels.
AI Scribe
Documents clinical encounters and maintains accurate EHR/EMR records in real-time.
AI Medical Coder
Assigns and validates medical codes to ensure accurate billing and regulatory compliance.
AI Nurse
Assesses patient urgency and coordinates appropriate care pathways based on clinical needs.